Quick version
In celiac disease, gluten damages the small intestine, making it difficult for the body to absorb iron, folate and vitamin B12. The disease therefore often manifests itself as persistent fatigue, mouth ulcers or low blood counts rather than clear stomach problems. If your values do not rise despite supplements, it may be due to poor absorption. Eat gluten as usual until the investigation is complete - once the diagnosis is made, the intestine heals with a gluten-free diet, although supplements may be needed at first.
Do you have low blood counts, fatigue that doesn't quite go away or an iron level that drops despite taking supplements? Many people first think of stress, heavy periods or a "slightly poor diet". But sometimes the explanation lies higher up in the gut. Celiac disease and nutritional deficiencies are often linked, and a lack of iron, folate or vitamin B12 can be the first signs before the stomach has even started to protest.
Why can celiac disease cause nutritional deficiencies?
Celiac disease is an autoimmune disease in which gluten triggers inflammation in the lining of the small intestine in people with the disease. When the intestinal villi are damaged, the body's ability to absorb nutrients from food is impaired, especially in the upper part of the small intestine where several important vitamins and minerals are normally absorbed.
This means that nutritional deficiencies are sometimes the first thing to notice. A person may seek treatment for fatigue, paleness, dizziness or recurring mouth ulcers without themselves connecting the problems to the gut. Celiac disease should be considered in cases of unexplained iron, folate or vitamin B12 deficiency.
This is a common reason why celiac disease is missed. Many adults do not have obvious diarrhea or classic stomach problems, but more discreet symptoms such as low energy, brain fog or difficulty recovering from exercise and everyday life.
Iron deficiency in celiac disease – often the first finding
Iron deficiency is one of the most common deficiencies in celiac disease and can be present both with and without anemia, i.e. anemia. Iron is needed to form hemoglobin, the protein in red blood cells that transports oxygen. When iron levels drop, you may feel tired, short of breath, have palpitations, headaches or difficulty concentrating.
In practice, it often looks like this: you are told that your ferritin is low, start taking iron tablets and perhaps feel a little better, but the values do not rise as expected. Then you need to consider whether the body can really absorb the iron. In the case of celiac disease, the answer is sometimes no, because the intestinal mucosa is still inflamed.
Iron deficiency in menstruating women is often explained by blood loss, which is sometimes true. But if the deficiency is pronounced, recurs or does not improve despite treatment, you need to think more broadly. Celiac disease can also be present when another possible explanation also exists.
Folate and B12 – small vitamins with great importance
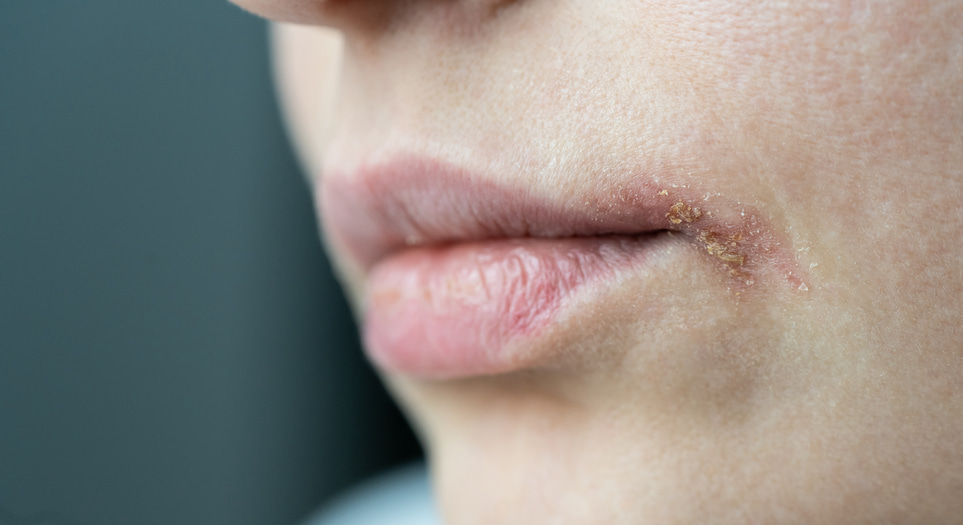
Folate, previously called folic acid in everyday language, and vitamin B12 are needed for cell division, blood formation and the function of the nervous system. A deficiency in any of them can cause anemia, but also symptoms that do not always look “blood-related”: tingling in the hands and feet, burning tongue, mouth ulcers, memory impairment and unusual fatigue.
Folate deficiency is logical in celiac disease because folate is absorbed in the proximal small intestine, i.e. the part that is often affected early in the disease. B12 is mainly absorbed further down in the small intestine, but B12 deficiency still occurs in some people with celiac disease, probably through a combination of malabsorption, simultaneous intestinal involvement and sometimes other autoimmune conditions.
When both folate and B12 are low, the blood picture can be difficult to interpret. Some people get large red blood cells, others not at all. If iron deficiency is present at the same time, the typical laboratory patterns can also be hidden. Therefore, it is not always enough to just look at Hb; it is often necessary to assess several samples together.
What symptoms should raise suspicion of celiac disease and nutritional deficiency?
There is no single symptom profile that fits everyone. Some have clear stomach problems, while others primarily notice the effects of slow nutritional deficiency. Serological testing for celiac disease should be offered in cases of, among other things, prolonged fatigue, unexplained stomach upset, weight loss, recurrent mouth ulcers and unexplained deficiency of iron, folate or vitamin B12.
Common situations where celiac disease may be worth considering are:
- iron deficiency that recurs despite treatment
- anemia without a clear explanation
- fatigue together with low ferritin, low folate or low B12
- stomach upset in combination with mouth ulcers, bloating or loose stools
- neurological symptoms such as tingling or numbness simultaneously with vitamin deficiency
This applies even if you are not underweight. Celiac disease can be found in people with completely normal weight, and sometimes the disease is only discovered when abnormal blood tests are investigated.
How is celiac disease investigated when the tests show a deficiency?
The first step is usually a blood test for celiac antibodies, most often IgA antibodies against tissue transglutaminase, often together with total IgA so as not to miss IgA deficiency. If the blood test indicates celiac disease, further treatment is carried out according to healthcare routines, sometimes with additional tests and sometimes with a small intestinal biopsy to confirm the diagnosis. It is also important to continue eating gluten until the investigation is complete, otherwise the test results may be misleading.
At the same time, nutritional status is usually assessed. In celiac disease, it is recommended to assess deficiencies such as iron, folate, vitamin B12, vitamin D and sometimes calcium at diagnosis and during follow-up. This gives a clearer picture of how much the body has been affected and what supplements are needed during healing.
Hb shows if you have anemia, ferritin reflects iron stores, and folate and B12 help explain fatigue, mucous membrane problems and neurological symptoms. In some cases, MCV, transferrin saturation, or homocysteine are also relevant to the overall picture.
What happens to iron, folate, and B12 after diagnosis?
The treatment for celiac disease is a strict gluten-free diet. As the inflammation in the small intestine heals, nutrient absorption gradually improves, and many people then have better iron status and better levels of folate and B12. For iron deficiency anemia in celiac disease, gastroenterological recommendations emphasize that good adherence to a gluten-free diet is central to recovering iron absorption.
However, the improvement is not always immediate. Some people need iron, folate or B12 as a supplement for a period, and sometimes longer than initially thought. In the case of B12 deficiency due to malabsorption, injection treatment may need to be considered instead of tablets alone, depending on the degree of deficiency and how the body responds.
There is also a practical pitfall: a gluten-free diet is not automatically nutritious. Many gluten-free industrial products are based on refined starch and may contain less of certain B vitamins and minerals than regular grain products. Therefore, it is not always enough to simply “remove gluten” — the diet also needs to be well-composed.
For those of you who already have known celiac disease but are still tired, it may be wise to check your values again. Persistent low ferritin or vitamin deficiency does not necessarily mean that the diagnosis is wrong, but it signals that the body still needs support, follow-up or a review of the diet.
Celiac disease is not always visible on the outside. Sometimes it is only when the iron stores are depleted or when the nervous system begins to react to B12 deficiency that the body sends a clear signal. That is why a blood test can be the beginning of an important discovery, not just a check of individual numbers.